
How Far Will Insurers Go To Offset Your Benefits?
We have previously discussed benefit offsets, which are provisions in policies that permit the insurer to reduce the amount of your monthly benefits if you are receiving income from certain sources (listed in the policy). While you may be aware that these provisions exist, you may be shocked by how far some insurers are willing to go to reduce benefits.
In the case of Rustad-Link v. Unum[1], Dawn Rustad-Link suffered a below-the-knee amputation after receiving negligent medical care. In addition, she had been diagnosed with multiple sclerosis (MS) several years earlier. Accordingly, she filed for disability benefits under her Unum policy.
At the outset of Rustad-Link’s claim, Unum determined that her MS was the primary disabling condition, and asserted that she had to wait 12 months to receive benefits, because the MS was a pre-existing condition.
Later on in the claim, Rustad-Link received a medical malpractice settlement (in connection with the below-the-knee amputation). When Unum learned about the settlement, it changed it’s prior assessment, determined that the amputation (not the MS) was the primary disabling condition, and asserted that, because of this, they were entitled to offset any income she received as a result of the amputation (i.e. the medical malpractice settlement). Significantly, when asked to assess the situation, Unum’s own in-house attorneys concluded that the settlement proceeds did not qualify as an offset; however, Unum’s “Financial Recovery Unit” ignored this, and continued its efforts to apply and enforce the offset. Unum then claimed that it had overpaid roughly $47,000 in benefits, and informed Rustad-Link that, moving forward, it would be reducing her benefits each month by roughly $2,000 until this amount was repaid to Unum (resulting in a remaining monthly benefit of only $115). Rustad-Link then filed suit to contest Unum’s determination.
Fortunately, the Court saw through Unum’s efforts to improperly apply the offset and concluded that Unum’s interpretation of the policy was “impermissibly self-serving.” In reviewing the record, the Court noted that Unum did not change its assessment until after it learned of the medical malpractice settlement, and concluded that the only purpose behind this change was “to take advantage of the settlement by treating the entirety of her misfortune as income.”
Although, in the end, Rustad-Link was able to avoid an offset, this case highlights the fact that insurance companies are financially motivated to deny and/or reduce your disability benefits, and illustrates how far insurance companies are willing to go to apply an offset. This case also shows that, while many juries have awarded damages and regulators have imposed fines in an effort to deter to bad faith conduct, Unum (and other insurance companies) continue to take aggressive and unreasonable positions in order to benefit their bottom-lines.
[1] Rustad-Link v. Providence Health & Serv., No. CV 16-136-M-DWM, 2018 WL 651833 (D. Mont. Jan. 31, 2018).
Disability Insurer Profiles #1: AIG
The American International Group first began operating as a small general insurance business in Shanghai, China. Since then, AIG has acquired at least nine major insurance companies and now operates worldwide. AIG was frequently in the news about ten years ago, when the United States government paid $182 billion to bail out the company.[1] AIG has since recovered, reporting about $498.3 billion in total assets in 2017.[2]
If you have an AIG policy, it is important that you review and understand how the policy defines your “occupation” in the context of a disability claim. Many physicians think their occupation will be defined as what they put down on the initial policy applications, or think it means the “primary” occupation that they are engaged in. However, under most disability policies (particularly newer disability policies), that is not how “occupation” is defined. Under most disability policies, your occupation can change if you take on new responsibilities and/or new positions prior to filing your disability claim.
For example, the case of Hayes v. AIG[3] involved a physician who filed a “total disability” claim for severe back pain, neck pain, and numbness following a head injury. When he filed his claim, the doctor identified his occupation as “physician” with a specialty of “occupation medicine.” However, in addition to his duties at the hospital, the doctor also worked part-time performing acupuncture. At some point after being awarded “total disability” benefits, the doctor returned to work. The doctor maintained he was working in a different capacity than his specialty of “occupation medicine”; however, the work included acupuncture.
The policy defined “current occupation” as “the duties of the medical specialty then being practiced or of the occupation being performed immediately prior to the disability” (emphasis added). AIG argued that this definition encompassed all of the duties the doctor engaged in prior to disability, including acupuncture, and maintained that the doctor’s return to acupuncture precluded a finding of “total disability.”
This particular case was hard-fought by both sides, and when the doctor’s attorney sued AIG, the court ultimately ruled against the doctor on several other legal issues. But this back-and-forth regarding how this definition of “occupation” should be interpreted illustrates why it is important to understand what your policy says before filing, if you want to avoid costly, time-consuming litigation.
With respect to AIG’s claim administration, AIG often pays doctors to evaluate claims made under its policies. These doctors are usually asked to conduct “file reviews” of the available medical records and render an opinion, without personally examining the claimant.[4]
In some instances, insurance companies use these “file reviews” as a basis for generating follow-up questions and/or justifying requests for in-person medical examinations. But, in other instances, you may not find out that the reviewing doctor was looking at your records until you receive notice that your claim is being terminated or denied. Accordingly, it is important that your symptoms, limitations and treatment are all consistently and accurately reported in your medical records.
These are just a few examples of things to be aware of if you have an AIG policy or claim with AIG. Not all AIG policies are identical, and they are updated frequently. Your policy may or may not include the provisions mentioned above. If you are considering filing a disability claim, you should consult with an experienced disability insurance attorney to learn more about your policy and any potential issues related to your particular claim.
[1] https://www.treasury.gov/press-center/press-releases/Pages/tg1703.aspx
[2] http://annual.aig.com/ui/2017/docs/AIG-2017-Final-Annual-Report.pdf
[3] See Hayes v. Am. Intern. Group, 2014 WL 3746813 (E.D. Penn. July 29, 2014).
[4] See, e.g., Adair v. El Pueblo Boys & Girls Ranch, Inc., No. 11-CV-02749-WYD-KLM, 2013 WL 4775927 (D. Colo. Sept. 5, 2013).
Do You Have A Specialty-Specific Policy?
Your ability to collect disability benefits under your insurance policy depends first and foremost on how “total disability” is defined under your policy. As we have previously discussed, if you are a professional choosing a policy, you will want to look for a policy that defines “total disability” in terms of your inability to perform your “own occupation,” and you will want to be sure to look for a true “own-occupation” policy.
While most professionals are aware of the importance of seeking out an “own-occupation” policy, you may not be aware that insurance companies also offer specialty-specific own occupation policies that are tailored to physicians and dentists who are specialists. These policies have a more precise definition of “total disability” that requires the insurance company to not only consider your occupation, but also your specialty when assessing eligibility for disability benefits.
Here’s a few examples of what these specialty-specific policies look like:


Oftentimes, the premiums charged for these types of policies are higher than other policies, but if you end up needing to file a claim down the road, and you are a physician or dentist with a board recognized specialty, this type of “total disability” provision can help ensure that your specialty (and corresponding job duties) are given proper weight. If you have a specialty-specific definition, and your insurance company is not taking into consideration the unique demands and duties of your specialty, you should contact an experienced disability insurance attorney and he or she can ensure that this important provision is enforced.
What is an EMG?
Most people are familiar with CAT scans or MRIs. EMG tests are another diagnostic tool that are, perhaps, not as well known.
What Is An EMG/NCS?
EMGs and Nerve Conduction Studies (NCSs) are diagnostic procedures that are often done at the same time and are used to assess the health of the muscles and the nerve cells (motor neurons) that control them. Because motor neurons transmit electrical signals that cause muscles to contract, an EMG can record these and turn the signals into sounds, graphs, or numerical values to be interpreted.
During an EMG, a needled electrode is inserted into a muscle to record the electrical activity. The activity is recorded muscle during rest, slight contraction, and forceful contraction. This data used to help detect any neuromuscular abnormalities.
In a NCS, electrodes are taped to the skin and the speed and strength of signals between two points is measured. When a signal travels at a slower rate that it should, the nerve may be damaged.
Why Might Your Doctor Order An EMG/ NCS?
Typically, these tests are used to diagnose a nerve or muscle disorder, so a doctor may order them if he/she is looking for an explanation for the following:
- Tingling
- Numbness
- Muscle weakness
- Muscle pain or cramping
- Some types of limb pain
- Involuntary twitching
- Paralysis
What Are EMGs Used For?
They are used, in connection with other tests, to diagnose or rule out muscle disorders, nerve disorders, or disorders affecting the connection between the two, including:
- Muscular dystrophy
- Radiculopathies (when it involves motor fibers)
- Herniated discs
- Spinal stenosis
- Carpal tunnel syndrome
- Cubital tunnel syndrome
- Neuropathies
- Pinched nerves
- ALS
- Guillain-Barre syndrome
- Myasthenia gravis
- How well a patient is recovering from a nerve injury
While who is authorized to perform EMGs varies by state, EMGs/NCSs are typically performed by a specialist or a specially trained physician, usually a neurologist, qualified to interpret the data.
These posts are for informative purposes only and should not be used as a substitute for consultation with and diagnosis by a medical professional. If you are experiencing any of the symptoms described above and have yet to consult with a doctor, do not use this resource to self-diagnose. Please contact your doctor immediately and schedule an appointment to be evaluated for your symptoms.
References:
Mayoclinic.com
Webmd.com
Healthline.com
Providence.org
Edward O. Comitz Named Southwest Super Lawyer for 2018

Ed Comitz has been named a 2018 Southwest Super Lawyer for excellence in the field of insurance for the seventh consecutive year.
Super Lawyers is a rating service of outstanding lawyers from more than 70 practice areas who have attained a high-degree of peer recognition and professional achievement. Only 5% of attorneys in the Southwest receive this distinction. The selection process is comprised of independent research, peer nominations and peer evaluations.
Am I Under Surveillance?
In previous posts we’ve looked at when disability insurance companies are most likely to conduct surveillance of claimants and new technologies that they’re deploying to do so. Surveillance is a common tool used by disability insurance companies in the claims process. Disability insurers claim that surveillance is merely used as a fraud prevention tool to ensure that claimants’ disabilities are legitimate.
Unfortunately, more often it is used to distort the true nature of the claimant’s disability and deny legitimate disability claims through photos, videos, and observations by investigators that are intentionally taken out of context. Even if your limited activity is consistent with your disability, a photo or five-second video clip can paint a misleading picture. Insurers can use this information to terminate disability benefits, shifting the burden to you to prove that the surveillance is not representative of your disability. This process can drag on for long periods of time – during which you are not receiving your monthly disability benefits.
An insurance company’s investigators may employ a number of different tactics during surveillance of claimants. In this post we’re going to take a look at several of these tactics and discuss some of the signs that may indicate you are under surveillance.
Social Media
Social media monitoring has become one of the most prominent methods of surveillance used by disability insurers during the claims process. Disability insurance companies hire tech-savvy millenials to comb the Internet and social media websites for photos, videos, and posts they can use against you. They will also look for patterns in your photos, check-ins, and posts to better predict where you are at any given time for in-person surveillance.
As a general rule of thumb for social media, you should adjust your privacy settings on Facebook, Instagram, Twitter, and other sites to allow only approved people to view your profile, your posts, and your photos/videos. Some social media sites have separate privacy settings for your profile and your photos/videos – be sure to take a careful look at how the privacy settings on each site are organized so you’re covering all your bases.
If you receive a friend request from somebody you don’t recognize, it is better to err on the side of caution and reject the request.
“Interview” by Investigator
One of the most obvious and most common signs that you are under surveillance is an investigator sent to your house by the disability insurance company to “interview” you. During this interview, they may ask you what you do every hour of the day under the pretense that the insurer needs a better idea of how your disability affects your daily activities. They may also ask to take a picture of you or take a photocopy of your driver’s license for “the file.”
These requests may seem harmless, but they have an ulterior motive. The purpose asking what you do every hour of the day isn’t to get a better understanding of your disability, it’s to help the investigator get an idea of where you are at any given time so they can conduct more effective surveillance. The purpose of taking your photo or asking for a copy of your driver’s license isn’t simply for the file – it’s to help investigators more readily identify you when you are out in public.
Unusual Telephone Calls
If you or your family members begin receiving telephone calls from unusual phone numbers, you might be under surveillance. Investigators will sometimes call a number associated with you, your residence, or your family members, ask for you, and hang up after they get a response. This tactic is used to determine whether or not you are home, and if not, to get an idea of where you are so they can conduct surveillance. If you are able to, keep track of any phone numbers from which you receive multiple suspicious calls, and create a list of Do-Not-Answer phone numbers.
Unusual Vehicles Outside Your House
Investigators are known for sitting outside claimants’ houses for hours at a time to get photos and videos of claimants doing activities around the house and in the front yard. If you see an unfamiliar car parked on the street near your house for long periods of time, it may be an investigator hired by your disability insurance company. Occasionally they will put up “blackout” shades in their windows when they park so you cannot identify them, and in some cases will actually go as far as removing their license plates while parked. If you see a vehicle like this parked near your house, we suggest closing your blinds and avoiding any activity in the front yard.
Unusual Driving Behavior
Another common surveillance tactic used by investigators is “tailing” claimants. An investigator may follow a claimant for hours at a time as he or she drives around going about their daily activities. Like home surveillance, tailing creates many opportunities for an investigator to snap a quick video or photo that the disability insurer can use to misrepresent your disability. If you see a suspicious vehicle following you too closely, changing lanes when you change lanes, or exhibiting other unsafe driving behavior, it may be an investigator from your disability insurance company.
The safest way to determine whether or not you are being followed is to make three consecutive right turns. If the suspicious vehicle follows you through all three turns, you are likely being followed. If you are being followed, do not engage in unsafe driving behavior or attempt to confront the other driver. It is better to simply return to your home. If their driving behavior is unsafe or makes you uncomfortable, don’t hesitate to call the police.
Strangers at Your Door
Investigators are known to come to claimants’ doors posing as door to door salesmen or community members gathering signatures for petitions. Like many of the other tactics, this is intended to give the investigator a closer look at your body movements, your posture, and your behavior. If you see somebody unfamiliar at your door, ask a few questions through the door about the purpose of his or her visit before you open the door. If the answers do not satisfy you, simply ask them to leave.
Rule Number One
With any of these surveillance tactics, the most important thing to remember is that if you feel uncomfortable or unsafe, you have every right to call the police. Your disability insurance company has the right to conduct surveillance as long as they obey the law. However, they do not have the right to trespass, endanger your safety or your family’s safety, or harass you. If you think you may be under surveillance or have any questions about the tactics being used by your insurer, contact an experienced disability insurance attorney.
Cubital Tunnel Syndrome
In previous posts, we’ve discussed several chronic conditions that can affect dentists in particular, as their jobs require them to hold unnatural, static positions for extended periods of time while continuously gripping instruments. This puts tremendous stress on their musculoskeletal systems, especially their hands, and this is, in part, why dentists experience nearly four times the prevalence of hand, wrist and arm pain found in the general public.
While most dentists and surgeons are likely familiar with carpal tunnel syndrome, there are other conditions affecting the hands that can be just as debilitating. In this post we will examine the causes, diagnosis, symptoms, and treatment of cubital tunnel syndrome, a similar condition that arises from nerve impingement at the elbow.
Overview
Cubital tunnel syndrome is a condition that involves pressure or stretching of the ulnar nerve (also known as the “funny bone” nerve) that runs in a groove on the inner side of the elbow. This can cause numbness or tingling in the ring and small fingers, pain in the forearm, and/or weakness in the hand. Those suffering from cubital tunnel syndrome can find it difficult or impossible to function with the same level of dexterity that they used to have.
Causes
Cubital tunnel syndrome occurs when the ulnar nerve becomes compressed or irritated at the elbow, but the exact cause of this is often unknown. There are several factors that can lead to nerve irritation such as:
- Keeping your elbow bent for long periods of time
- Repeatedly bending your elbow
- Leaning on your elbow for long periods of time
- Repetitive activities that require the elbow to be flexed
- Prior fractures or dislocations of the elbow
Diagnosis
In order to diagnose cubital tunnel syndrome, a physician will perform a medical history review and physical examination. The examination will include an evaluation of the sensation of the hand and fingers as well as a test of your elbow reflex. Additional screening may be required, including:
- X-rays: to check for bone spurs, arthritis, or other places that the bone may be compressing the nerve
- Nerve conduction studies: to determine how well the nerve is working and to help identify where it is being compressed
- Electromyogram: a test that measures the electrical discharges produced in the muscles
Symptoms
Generalized symptoms of cubital tunnel syndrome include:
- Numbness and tingling in the ring finger and pinky finger, usually occurring when the elbow is bent (such as when driving or holding a phone)
- Feeling of pins and needles or the feeling of the hand “falling asleep” in the ring and pinky finger
- Weakening of the grip and difficulty with finger coordination, especially when manipulating objects
Severe symptoms can include:
- Weakness in the ring and little fingers
- Decreased hand grip
- Muscle wasting in the hand
- Curling up of the pinky and ring finger along with pain, or a claw-like deformity of the hand
Treatment
Mild symptoms of cubital tunnel syndrome can be managed with home remedies such as:
- Avoiding activities that require you to keep your arm bent for long periods of time
- Avoiding leaning on your elbow or putting pressure on the inside of your arm
- Keeping your elbow straight at night when sleeping by wrapping a towel around your elbow or wearing an elbow pad backwards
- Performing nerve gliding exercise
More severe cases of cubital tunnel syndrome may require medical interventions such as:
- Use of non-steroidal anti-inflammatory drugs (NSAIDs) to reduce swelling around the nerve
- Use of corticosteroids
- Bracing or splinting
- Surgery to increase the size of the cubital tunnel or to transpose the nerve in order to relieve the pressure
These posts are for informative purposes only and should not be used as a substitute for consultation with and diagnosis by a medical professional. If you are experiencing any of the symptoms described above and have yet to consult with a doctor, do not use this resource to self-diagnose. Please contact your doctor immediately and schedule an appointment to be evaluated for your symptoms.
References:
American Society for Surgery of the Hand, http://www.assh.org
American Academy of Orthopaedic Surgeons, https://orthoinfo.aaos.org/
Mayo Clinic, www.mayoclinic.org
WebMD, www.webmd.com
Healthline, www.healthline.com
Dental Products Report, dentalproductsreport.com
Multiple Sclerosis
Multiple sclerosis (MS) is a disease of the central nervous system, which is made up of the brain, spinal cord, and optic nerves. It’s estimated that 2.3 million people worldwide have MS. In this post we’ll examine the symptoms, causes, diagnosis, and treatment of this disease.
Overview
With MS, the immune system begins to attack the protective sheath, called myelin, that covers the nerve fibers. The result is faulty communication between the brain and the rest of the body. The disease may eventually cause the nerves deteriorate and they may even become irreversibly damaged.
The symptoms experienced and the rate of progression and severity of the disease will vary greatly from person to person. Some individuals may have a very minor form of MS, while others will go on to become paralyzed, or, in rare instances, have a potentially fatal form that progresses rapidly from onset.
MS has several difference courses, in terms of how the disease progresses:
Relapse-Remitting MS: Most people with MS experience times of new symptoms, or relapses, that develop in a relatively short period of time followed by periods remission where there are few or no symptoms.
Secondary-Progressive MS: About 60 to 70% of people with relapse-remitting MS type will go on to experience a steady progression of symptoms.
Primary-Progressive MS: Some individuals have a gradual onset and progression of symptoms without relapses.
Benign MS: MS is considered benign if the individual has no relapses and a mild, stable disability after about 15 years from the time of diagnosis.
Symptoms
Because MS attacks the central nervous systems, a wide range of symptoms in nearly any function can occur. Symptoms will also vary in type and severity from one person to another. Symptoms can resolve, come and go, or be permanent. Common symptoms include:
- Blurred vision
- Partial or complete loss of vision
- Loss of balance
- Poor coordination
- Dizziness or vertigo
- Slurred speech
- Tremors
- Tingling
- Electric shock sensations
- Numbness or weakness
- Extreme fatigue
- Depression
- Temperature sensitivity
- Memory and concentration problems
- Paralysis
Causes and Risks Factors
While the cause of MS is unknown, many believe it is a mix of genetics and environmental factors. Scientists have identified several risk factors that may be associated with MS:
- Genetics and family history
- Gender (women are 2 to 3 times more likely to develop MS)
- Age (most people are diagnosed between the ages of 20-50)
- Certain infections, including the Epstein-Barr virus
- Certain autoimmune diseases, including type 1 diabetes or thyroid disease
- Smoking
Diagnosis
MS is often a hard disease to diagnose, especially because symptoms vary from person to person, can come and go, and are similar to other disorders of the nervous system. While there is no single diagnostic test, there are several methods physicians use to evaluate individuals for MS, including:
- Blood tests to screen for other diseases with similar symptoms (e.g. Lyme disease)
- Balance, coordination, vision, and other tests to see how the nerves are functioning
- MRIs to detect changes in the brain (lesions) and/or spinal cord
- Evoked potentials tests, which evaluate electrical activity in the brain
- Analysis of the cerebrospinal fluid (CSF) in the brain and spinal cord for specific proteins
- Spinal tap to look for abnormalities in antibodies, and look for infections or other conditions with similar symptoms
Treatment
At present, there is no cure for MS. However, there are several treatments doctors utilize in an effort to manage symptoms, shorten the length of attacks, and modify the progression of symptoms. Some of them are listed below.
Treatment to Modify Progression
- Medications to curb the body’s immune system to attempt to stem the body’s attack on the myelin
Treatment for MS Attacks
- Corticosteroids to reduce nerve inflammation
- Muscle relaxants
- Plasma exchange
Treatments for Symptoms
- Medications (fatigue, depression, and other symptoms)
- Muscle relaxants
- Physical therapy
- Staying cool, sometimes with devises such as a cooling vest (symptoms often worsen when body temperature rises)
- Alternative medicine (acupuncture, massage, relaxation techniques)
- Exercise and reducing stress
Treatment will often involve an interdisciplinary approach and may require treatment from a care team including neurologists, physiatrists, urologists, psychiatrists, physical and occupational therapists, and others as needed.
These posts are for informative purposes only and should not be used as a substitute for consultation with and diagnosis by a medical professional. If you are experiencing any of the symptoms described below and have yet to consult with a doctor, do not use this resource to self-diagnose. Please contact your doctor immediately and schedule an appointment to be evaluated for your symptoms.
References
National Multiple Sclerosis Society, https://www.nationalmssociety.org
Mayo Clinic, https://www.mayoclinic.org
John Hopkins Medicine, https://www.hopkinsmedicine.org
WebMD, https://www.mayoclinic.org
Firm Named #1 Law Firm for Best Workplace Culture
We are proud and honored to announce we have been named Arizona’s #1 Law Firm for Best Workplace Culture and the #2 firm in both Healthcare Law and Firm with Under 22 Lawyers by Ranking Arizona: The Best of Arizona Business. Ranking Arizona publishes the results of the largest annual poll of the Arizona business community. Residents are asked to share their opinions of the best products, services, and individuals in the state.
We’ve earned this distinction through the development and execution of studied, meticulously considered strategies aimed at obtaining optimal results for our clients. We have also remained a small firm in order to encourage the sharing of ideas and information in an environment fostered by mutual trust. We pride ourselves on recruiting only the top attorneys in education, skills, and temperament.
We offer dentists, physicians, and other professionals compassion, thoughtful and meticulous legal representation, and are dedicated to making the claims process as painless as possible for each client. Our Firm offers unparalleled strategy, advocacy, and adaptability. Our clients have immediate attorney access, including their direct telephone lines and emails. Each case has a minimum of two attorneys and a paralegal working on it, with senior partners directly involved in developing each case.
Our keen legal, medical, and disability industry insight allows us to know what really matters in a case, and we are able to leverage this experience to deliver success. We are pleased that our dedication has earned us this recognition for both our legal expertise and our firm’s collaborative ethos, which allows us to work together tirelessly in order to exceed our clients’ most optimistic expectations.
Why You Can’t Blindly Rely on Your Agent to Choose the Right Policy for You
In earlier posts we’ve discussed how agents don’t have the authority to change, delete, or add provisions to a disability insurance policy. We’ve also discussed how most disability insurance policy applications now contain language stating that you cannot rely upon representations made by agents regarding the scope of coverage, or eligibility for coverage. Thus, while agents can provide helpful advice and help to point you in the direction of a disability insurance policy that may fit your needs, it is ultimately up to you, the purchaser, to review your policy, become familiar with the provisions of the policy, and confirm that you are in fact purchasing the coverage that you expected to receive.
If you don’t take the time to do this, and blindly pay premiums without reviewing your disability insurance policy first, you could end up paying for coverage that provides less protection than you thought you were getting when you applied for the policy. For example, most physicians and dentists know that their disability insurance policies should be “own occupation”, meaning a policyholder is considered totally disabled (and eligible to collect benefits) when he or she can no longer work in his or her profession, versus being unable to work at all, in any profession. In some policies, own occupation is further defined as being unable to practice in a particular medical or dental specialty (i.e. anesthesiologist, periodontist, etc.).
Quite often physicians and dentists decide to buy another policy, either because they let a previous one lapse, or because they want to purchase additional coverage as their income increases and they can afford higher premiums, and they ask their agent for a new policy with the “same coverage”. This can be incredibly difficult or impossible to achieve, because over time disability insurance policies have evolved to become more restrictive, and each company has variations on what they deem an “own occupation” policy. Consequently, while your agent may present you with a policy that contains the phrase “own occupation”, it may not be a true own occupation policy at all.
For example, some policies are actually conversion policies, which mean they start out as “own occupation” policies, but after a certain time frame (e.g 2 years, or 5 years), they change to an “any occupation” policy, which means that, in order to continue receiving disability benefits, you would have to show that you can’t work at all. This can be very difficult to prove, particularly if you worked in another capacity for all or some of the prior “own occupation” period.
Even if your agent does locate an own occupation plan with similar premiums and benefit amounts to an older policy, there may also be provisions that cancel each other out in the new and old policies. One scenario we’ve seen is a disability insurance policy containing the provision that a claimant must not be working (a “no work” provision) in their own occupation or another profession in order to collect benefits, while the second policy states that a claimant must not be working in their own occupation but must be working in another field in order to collect benefits (a “work provision”). Under this scenario, in essence, one of the policies you’ve been paying years of premiums for is worthless, as both requirements cannot be met at once.
These examples highlight why it is important that you do more than just check an “own-occupation” box on your application and/or blindly rely on your agent’s assurance that a new policy is compatible and/or the same as an existing one. If you end up with a policy you essentially cannot use, your recourse is limited, as insurance companies have gone to significant lengths to shield themselves from any liability based on an agent’s representations of a policy. It is therefore far better to take the time to review your policy at the outset, before you pay years of premiums, to ensure that it provides the disability coverage that you applied for and need.
Diabetes: An Overview
We’ve talked before about how diabetes can occur in conjunction with other diseases, such as anxiety, or contribute to certain medical conditions, such as radiculopathy. In this post we will be taking a broader look at diabetes and its complications.
Overview:
Diabetes (diabetes mellitus) refers to a group of diseases, including prediabetes, type 1, type 2, and gestational diabetes. While prediabetes and gestational diabetes can be reversible, types 1 and 2 are chronic and there is currently no cure.
Diabetes can occur either when the pancreas produces very little or no insulin, or when the body does not respond to the insulin that the pancreas does produce. In this post we will examine only types 1 and 2.
Type 1 diabetes typically appears during childhood or adolescence (it is also called juvenile diabetes), and the symptoms come on quickly and are more severe. Type 2 diabetes is more common, and more often occurs in people over 40 (it is often referred to as adult onset diabetes). Those with type 2 diabetes may not exhibit symptoms at first.
Symptoms:
- Increased thirst
- Extreme hunger
- Frequent urination
- Unexplained weight loss
- Ketones in the urine
- Fatigue
- Irritability
- Blurred vision
- Difficulty breathing
Additional symptoms experienced in Type 2 diabetes include:
- Cuts or sores that are slow to heal
- Infections
- Itchy skin (often in the groin area)
- Recent weight gain
- Numbness or tingling of the hands and feet
- Impotence or ED
Causes:
Type 1 diabetes occurs when the body’s immune system destroys the insulin producing cells of the pancreas. Scientists believe that Type 1 is caused by genetic and environmental factors, such as exposure to certain viruses.
Type 2 diabetes is caused primarily by lifestyle factors and genes. Some risk factors include:
- Being overweight
- Lack of physical activity
- High blood pressure
- Abnormal cholesterol and/or triglyceride levels
- Family history (having a parent or sibling with diabetes increases risk)
- Age
- History of gestational diabetes while pregnant
- Polycystic ovary syndrome
Diagnosis:
Diabetes can be diagnosed based on blood tests that show a patient’s blood sugar levels, using a glycated hemoglobin (A1C) test, random blood sugar test, fasting blood sugar test, and/or an oral glucose tolerance test.
With respect to type 1 diabetes, a patient’s urine will be analyzed for ketones, a byproduct produced when muscles and fat are used for energy when the body doesn’t have enough insulin to use available glucose.
Treatment:
While there is no cure for diabetes, ongoing monitoring and management of symptoms is required to prevent serious complications from occurring. Possible treatments include:
Lifestyle changes
- Diet/healthy eating
- Exercise
- Weight loss
Medication
- Those with Type 1 diabetes must take insulin because it is no longer made by the body
- Those with Type 2 may need to take insulin, but may also take different medications (such as metformin, which lowers the amount of glucose the liver makes)
Surgery
- Bariatric surgery
- Artificial pancreas
- Pancreatic islet transplantation
Serious Complications:
Undiagnosted, untreated, or resistant to treatment, diabetes can have serious health consequences, including:
- Cardiovascular disease;
- Nerve damage (neuropathy), especially in the limbs (which left untreated can result in loss of feeling); nerve damage is also connected to problems with internal organs, weakness, weight-loss, and depression;
- Kidney damage (nephropathy), which may result in the eventual need for dialysis or kidney transplant;
- Eye damage (retinopathy), which may result in cataracts, glaucoma, or blindness;
- Skin conditions, including bacterial and fungal infections;
- Foot damage, which can often lead to the need for amputation;
- Depression; and
- Alzheimer’s disease (type 2 diabetes)—currently there is no agreed upon theory about why there is a correlation between the two diseases.
These posts are for informative purposes only and should not be used as a substitute for consultation with and diagnosis by a medical professional. If you are experiencing any of the symptoms described below and have yet to consult with a doctor, do not use this resource to self-diagnose. Please contact your doctor immediately and schedule an appointment to be evaluated for your symptoms.
References:
Center for Disease Control (CDC), www.cdc.gov
WebMD, webmd.com
Mayo Clinic, mayoclinic.com
National Institute of Diabetes and Digestive and Kidney Disease, www.niddk.nih.gov
American Diabetes Association, www.diabetes.org
How Do I Know if My Insurer Might Be Interested in a Lump Sum Settlement?
We are often asked whether a particular claim is the type of claim that an insurance company would be interested in settling for a lump sum buyout. The answer, as explained in more detail below, is always, it depends, because there are a number of factors that come into play, and many of those factors are not even directly related to whether the claim itself is legitimate or whether the insured’s condition is permanent (although those are important factors that impact whether a buyout is a possibility).
What is a Lump Sum Buyout?
You may be familiar with the terms of your disability policy, but you may not know that, in certain instances, insurers are willing to enter a lump sum settlement. Under a lump sum settlement, your insurer agrees to buy out your policy and, in return, you agree to surrender the policy and release the insurer from any further obligations to you going forward.
There are certain pros and cons to this sort of settlement. Some claimants prefer a lump sum settlement, because it allows them to avoid having to rely on month-to-month payments from their insurer (which may or may not arrive, or if they do arrive, may not arrive on time) and/or to avoid the hassle of dealing with claim forms, medical exams, etc. for years to come. A lump sum settlement can also allow you to take advantage of present investment opportunities that can provide for your and your family’s future. But there are also other considerations that you will need to discuss with your attorney as well as your accountant and other financial advisors. For example, if your benefit period lasts to age 65 (and you end up living to the end of the benefit period), you would likely receive more money cumulatively over time if you stayed on claim and received monthly benefits in lieu of a lump sum settlement.
Lump sum settlements can also be attractive to insurance companies. A settlement can allow insurance companies to release money from their reserves and to eliminate administrative expenses associated with the ongoing review of your claim year after year. But just as you might receive more money cumulatively over time if you stayed on the claim, the insurer might benefit financially from not offering you a lump sum settlement. For example, if your policy provided for lifetime benefits, and you met an untimely demise, your insurance company’s obligation to pay benefits would cease, and they may end up ultimately paying out a lower amount in total monthly benefits than they would have if they paid out a lump sum settlement on your claim.
Because this process is completely discretionary on their part, insurance companies are very deliberate about offering lump sum settlements. Before doing so, they must weigh multiple factors including the following:
-
- Permanency. The insurer is more likely to offer a settlement if its actuaries determine that you will likely be on claim for the maximum benefit period.
-
- Reserves. Over the course of your claim, your claim’s reserves slowly peak as you are on claim for an extended period of time (and permanency is established) and then at some point, they start to diminish as the claim is paid out, and you get closer and closer to the end of the maximum benefit period. The insurer is more likely to offer a settlement when the reserves are at their peak (typically around 3-5 years into a claim), because that is when the insurance company would improve its bottom line the most by freeing up the reserves.
-
- Mortality/Morbidity Issues. The insurer is more likely to offer a settlement if its actuaries determine that you will probably live to the end of the maximum benefit period. Or if you have lifetime benefits, the insurer will estimate your lifespan based on your health history to determine whether it is financially beneficial for the company to offer a lump sum settlement.
-
- Offsets. The insurer is more likely to offer a settlement if it determines that you will probably not receive income in the future that would offset the benefit amount before the end of the maximum benefit period.
-
- Anticipated Gain. Companies will not offer a buyout unless they stand to save money in the long run, so they have their actuaries calculate how much of a gain (percentage-wise) the company would net if they settle the claim. Insurers often have internal financial objectives that impact the amount they are willing to offer on settlements such as requiring a net gain amount of a certain percentage (e.g. 35%).
-
- Cash Outflow. The insurer will be more or less willing to offer a settlement depending on their quarterly or even annual cash outflows. Thus, if a company had paid out a lot of buyouts recently, the company may not have enough cash available to offer additional lump sum settlements.
The bottom line is that offering a lump sum settlement is completely voluntary on the part of the insurer and doing so depends on the unique factual circumstances of your claim. Nevertheless, knowing the factors that insurers consider in making this decision can help you understand whether a lump sum settlement is appropriate in your case.
The Importance of Reviewing Your Policy Application
In our last post we discussed why you should not rely solely on your agent’s representations when purchasing a new disability insurance policy. It is similarly important that you not rely solely on your agent to complete the policy application.
While an agent may offer to help you by filling out the disability insurance application, this could end up negatively impacting a future claim or even voiding your policy down the road, if the application contains any errors or omissions. As explained in our prior posts, while it may seem like telephone interviewers, licensed representatives, agents, and medical examiners have significant control over the application process and whether you receive a disability insurance policy, many applications have language that explicitly limits your ability to rely upon representations made by such individuals, and expressly places the burden of reviewing the application for accuracy upon you (regardless of who completed the application). Below is a sample of policy language:

Thus, you may speak with several people during the application process, and give them the requested information, but it is ultimately up to you to make sure the information provided to the insurance company is correct. It is therefore very important that you read through your disability insurance application carefully to make sure it is complete and accurate before signing.
It is also very important that you carefully review your disability insurance policy when you receive it from the insurance company, and not just file it away without a second thought. When you receive your copy of the full policy, it will typically contain language stating that you have a certain time period (e.g. 10 or 30 days) to review the policy and return it to be voided if it does not contain the terms you expected. This clause will normally be found on the first page of the policy, and typically looks something like this:

If you decide to keep your disability insurance policy and do not send it back within this review period, you are bound by all provisions of the policy, regardless of whether you are actually aware of them or not. For instance, if you asked your agent for a certain provision and/or requested it on your disability insurance application, but the insurance company omits it for some reason, and you don’t catch it during this review period, you may end up paying years of premiums for coverage that is different than what you thought you had purchased. Similarly, if your policy contains an unfavorable provision that you didn’t know was going to be in the policy, you will still be bound by it unless you return the policy.
How Insurance Companies Distance Themselves from Agents (And Why It Matters)
Reading through contracts, especially lengthy insurance ones, can be time consuming. Many policies contain confusing language, terms of art, and often include supplemental riders that change the terms or definitions contained in the main body of the policy. But if you don’t read your disability insurance policy until it’s time for you to file a disability claim, you may be caught off-guard by what your policy actually says. This next series of posts will discuss the importance of taking the time to read through your policy, and will review some things to watch out for when you buy a disability insurance policy.
Dentists and physicians are often swamped with work, and rely heavily on insurance agents when selecting and purchasing a disability insurance policy. One scenario we commonly see is doctors requesting a disability insurance policy that is “the same” policy that the other doctors in the practice have. Another common scenario is the doctor who wants more disability coverage and just asks his or her agent for another disability insurance policy that is “like” his or her existing policy, or has the “same coverage” as his or her existing policy. What they don’t realize is that some of the same favorable terms may no longer be available in today’s policies. For example, while most older disability insurance policies contained “true own occupation” provisions, there are now several different variations of “own occupation” provisions, so if you just ask for an “own occupation” policy, you may not actually be receiving the disability coverage that you think you are.
It is also important to be aware that, over the years, disability insurers have sought to distance themselves from agents and now often go so far as to include clauses or statements in their disability insurance policies and applications that state no agent or broker has the authority to determine insurability or make, change, or discharge any contract requirement. Here’s an example of this type of policy language:

So what does this mean? It means that, while solely relying upon an agent’s assurance of the terms of a policy may have been a more acceptable (but not advisable) option in the past (when policies were often similar and generally favorable to policyholders), you can no longer solely rely upon your agent’s description of the policy. No matter how well-meaning or knowledgeable your agent may seem, ultimately, you are going to be on the hook if your disability insurance policy doesn’t say what you thought it said, so it is crucial that you carefully review your disability policy to ensure you are receiving sufficient coverage.
Our next post will discuss the importance of the disability application process and policy review period.
Radiculopathy
In previous posts, we’ve discussed chronic pain, including how chronic conditions can affect dentists. Dentists and surgeons have strenuous jobs that require them to hold unnatural and static positions for extended periods of time, putting stress on their musculoskeletal systems. Consequently, it is not uncommon for dentists and surgeons to experience spinal issues, including radiculopathy. In this post we will examine the causes, diagnosis, symptoms, and treatment of radiculopathy.
Overview
Radiculopathy is a condition caused by a compressed nerve in the spinal column. This pinched nerve can occur at any spot in the spine, but is typically found in the cervical or lumbar portions of the back and, less frequently, in the thoracic spine. Symptoms vary based on where the nerve roots are compressed; however, the roots typically become inflamed and cause numbness, weakness, and pain. Those suffering from radiculopathy can find it difficult or impossible to function with the same level of dexterity they used to have.
Symptoms
Generalized symptoms of radiculopathy include:
- Sharp or shooting pains in the back, arms, legs, or shoulders that may worsen during certain activities
- Weakness or loss of reflexes in the arms or legs
- Numbness of the skin or “pins and needles” sensations in the arms or legs
- Some individuals develop a hypersensitivity to light touch at the affected areas
The location of and specific symptoms will vary based on where the compressed nerve occurs:
- Cervical Radiculopathy: Pressure on a nerve root in the neck. Symptoms include weakness, burning or tingling sensations, or loss of feeling in the shoulder, arm, hand, or fingers.
- Lumbar Radiculopathy: Pressure on a nerve root in the lower back. Symptoms include pain, weakness, or numbness that starts in the lower back and radiates through the buttocks down the back of the leg.
- Thoracic Radiculopathy: A pinched nerve in the upper/mid back. Symptoms include pain in the chest or torso, which can be mistaken for shingles.
Causes
Radiculopathy is caused by the irritation or compression of the nerves where they exit the spine. This compression can occur in several ways:
- Disc herniation, osteophytes (bone spurs), osteoarthritis, or the thickening of the surrounding ligaments
- Scoliosis
- Inflammation due to trauma or degeneration
- Conditions such as diabetes, rheumatoid arthritis, and obesity
- Poor posture and/or repetitive movements
- Aging
- Genetic pre-disposition
Diagnosis
In order to diagnose radiculopathy, a physician will perform a medical history review and physical examination. The examination will include an evaluation of muscle strength, sensation, and reflexes to detect any abnormalities. Additional imaging may be required, including:
- X-rays: to identify trauma, osteoarthritis, or early signs of a tumor or infection
- MRI or CT scan: to look at the soft tissues around the spine (nerves, discs, ligaments, etc.)
- Electromyogram (EMG) and nerve conduction studies: to look at electrical activity along the nerve to identify any damage
Treatments:
The course of treatment for radiculopathy will usually start out conservative, but more aggressive treatment may be needed when pain persists.
- Medications
- Weight loss (if necessary) to reduce pressure on problem areas
- Physical therapy
- Avoiding activity that causes strain on the neck or back
- Chiropractic treatment
- Epidural steroid injection
- Surgery to remove the compression on the spine
These posts are for informative purposes only and should not be used as a substitute for consultation with and diagnosis by a medical professional. If you are experiencing any of the symptoms described below and have yet to consult with a doctor, do not use this resource to self-diagnose. Please contact your doctor immediately and schedule an appointment to be evaluated for your symptoms.
References:
MedicineNet, https://www.medicinenet.com/radiculopathy/article.htm#what_is_radiculopathy
John Hopkins Medicine, https://www.hopkinsmedicine.org/healthlibrary/conditions/nervous_system_disorders/acute_radiculopathies_134,11
WebMD, https://answers.webmd.com/answers
Heathline, https://www.healthline.com/health/radiculopathy#causes
Columbia Spine, http://columbiaspine.org/condition/radiculopathy/
Medical News Today, https://www.medicalnewstoday.com/articles/318465.php
Lump Sum Disability Benefit Rider
While, hopefully, your disability policy will provide sufficient income to meet your essential expenses if you have to file a claim, benefit amounts rarely provide monthly income that is comparable to what you earned while practicing. Additionally, many disability insurance policies have maximum benefit periods that expire at age 65 or 67, which means you will be without a monthly income for the remainder of your life if you haven’t established other financial resources. As we’ve discussed in previous posts, one option to ensure continued financial stability is to purchase a policy that includes lifetime benefits rider. Another option we are beginning to see offered with some policies is the lump sum disability rider benefit.
The lump sum disability benefit rider is designed to provide a one-time lump sum payment at the end of the benefit period, much like being able to access a 401(k) or other retirement account upon reaching retirement age. This lump sum can also help to offset expenses that may be more likely to arise later in life, like the costs of needed surgeries or other medical care.
While lifetime benefits work by paying a claimant a continuing monthly benefit after the normal expiration date of a policy, under this type of rider, the insurance company pays a one-time payment at the end of the policy’s benefit period. The payout will typically be a certain percentage of the benefit payments the policyholder received prior to the end of the maximum benefit period under the policy. This calculation includes payments received both while on total disability and residual disability, over the life of the policy, whether continuous or not.
For example, say a claimant received a monthly benefit payment of $5,000 per month (or $60,000 per year) and remains on claim from age 48 to the end of the benefit period (age 65, for example) or 17 years. If the lump sum benefit is equal to 35%, the claimant would receive a one-time payment of $357,000 (17 x $60,000 x .35).
It is also important to note that these riders typically require that a claimant receive a minimum threshold amount of benefits to qualify to receive the lump sum payment. For example, the qualifying amount may be set at $60,000. If the monthly benefit payment is $5,000 a month, the policyholder won’t be eligible for a lump sum payment unless he or she remains on claim for at least 12 months over the life of the policy.
Thus, with a lump sump benefit rider, the longer a policyholder stays on claim, the larger the lump sum payment will be. It therefore stands to reason that disability insurance companies have an even stronger than normal incentive to get a claimant off claim. As insurance companies often use aggressive tactics to investigate claims in order to find justification to terminate or deny disability claims in an attempt to save money, having a lump sum benefit rider could result in greater scrutiny of a policyholder’s claim, particularly before the qualifying amount is reached. However, unlike lifetime benefit rider options (which typically require a policyholder to continue to submit proof of loss for life in order to continue receiving lifetime benefits), the insurance company’s ability to scrutinize a claim ends upon the payment of the lump sum under a lump sum disability benefit rider.
Thus, as with all policy provisions, there are pros and cons to keep in mind, and deciding whether the lump sum disability benefit rider is the right policy for you requires careful consideration of what you can afford in premiums, your age, other sources of income you and your household have, and your plans for retirement.
Lifetime Benefits, Part 2 – Graded Lifetime Benefits
In our last post we discussed how it can be difficult to save for retirement if your only income is your monthly disability benefits. One way to help ensure financial security into retirement age is to purchase a lifetime benefit option with an individual disability insurance policy. While older policies often featured full monthly disability benefit payments for life, newer policies insert qualifiers that limit whether a claimant will actually receive the full benefit amount for his or her lifetime. Our last post looked at the injury versus sickness limitation. In this post, we will be taking a look at another provision that limits lifetime benefits: the graded benefit rider.
Graded Lifetime Benefit Riders
Under the graded benefit rider, claimants receive benefits for life, provided they are disabled prior to a specified age and remain continuously totally disabled. However, the amount of the monthly benefit they receive varies based on how old the claimant is at the onset of his or her disability.
For example, a disability insurance policy may have a benefit period that ends at age 65, with a graded lifetime benefit rider (sometimes called a “lifetime extension for total disability”) that will pay 100% of monthly benefits for life if the policyholder is disabled prior to age 46. However, if the policyholder becomes disabled after age 46, his or her lifetime benefits will only be a certain percentage of the monthly payment.
Below is a provision from an actual policy, illustrating how benefit amounts are calculated under this type of rider:
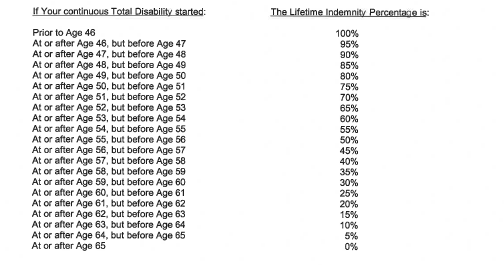
Using this chart as an example, if your benefit payments are $10,000 per month and you become totally disabled at age 46 (100% under the policy) your disability insurance company will continue to pay you $10,000/month after you turn 65 for the rest of your life. If you become totally disabled at age 55, the percentage of monthly indemnity payable would drop to 50% and your disability insurance company would pay you $5,000/month after you turn age 65. If you don’t become totally disabled until age 64, the amount payable would only be 5% of your monthly disability benefit. In other words, you would have a year or less of monthly payments of $10,000, followed by monthly payments of $500.
While a graded lifetime benefits rider is one way to ensure that you continue to receive disability income after your standard benefit period ends, you must keep in mind that these payments may not provide much income if you become disabled later on in life.
Further, in order to achieve lifetime benefits under this rider, you must remain totally disabled. So, for example, if you return to work, were pushed off claim, or went into residual disability claim status, you lose the lifetime benefits. And even if you are later able to reestablish total disability, the lifetime benefit will be a lower percentage of the monthly benefit, because you will have re-set your total disability date for purposes of calculating your monthly benefit under the rider.
Lifetime benefits offer a way for policyholders to continue to collect at least some income after the benefit period of their disability insurance policy ends. However, when choosing a disability insurance policy, physicians and dentists must carefully consider their age at the time of purchase, premium amounts, and the policy language before buying a policy. Knowing how your policy’s lifetime benefits work is an important step in planning for your financial future.
In our next post we will look at another option individuals have to supplement their retirement income: the lump sum benefit rider.
Lifetime Benefits, Part 1 – Injury v. Sickness Limitation
Having a disability insurance policy is an important step in protecting your financial security and ensuring a monthly source of income if you are forced to step away from practicing as a dentist or physician and file a claim due to a disability. However, as we’ve discussed before, your monthly disability benefits typically will not match the monthly income you were earning as a doctor, dollar for dollar. As a result, you may not have any funds left over, after your monthly expenses, to save for retirement. This can be problematic since many plans have a benefit period ending at age 65 or 67, but the average American life expectancy is around 79.[1]
There are a few options residents or doctors have when buying a disability insurance policy that can help ensure financial stability past retirement age. One option is selecting a policy with a lifetime benefit rider. Older disability insurance policies, from the 80’s and 90’s, were often drafted in policyholders’ favor and a lifetime benefit provision meant just that—full monthly benefits would be paid out until a claimant’s death. Many newer disability insurance policies still offer an option to purchase “lifetime benefits”, but there are additional qualifiers in the policy language that dictate the amount of the disability benefit the claimant will receive, or whether he or she will receive lifetime benefits at all. In our next few posts, we will look at two common lifetime benefit limitations that are common in newer disability insurance policies. In this post we will examine the injury versus sickness limitation.
Injury v. Sickness Limitation
Under some policies, the nature of your disability (i.e. whether your disability is caused by an “injury” or by “sickness”) can determine whether your benefits will last a lifetime. Here’s an example of such a provision, taken from an actual policy:

As you can see, under this policy’s language, you only receive lifetime benefits if your disability stems from an injury occurring before age 65. Further, no matter how permanent a sickness is, the policyholder will not be eligible to receive lifetime benefits under this disability insurance policy.
In some instances, it is very straightforward to determine when a disabling condition will be classified as an injury (e.g. the inability to walk after a car accident) or as a sickness (e.g. Parkinson’s disease). But in other instances, the distinction between the two becomes less clear and, in many instances, litigation is required to resolve the issue. If the date of an injury is not well-documented, or your limitations arguably have multiple causes, the insurance company will oftentimes elect to pay disability benefits under the sickness provision of your disability insurance policy, so they don’t have to pay lifetime benefits.
This provision highlights the importance of carefully documenting and filing your disability claim from the outset, in order to prevent any ambiguity in the nature of a disabling condition. It also highlights the importance of understanding the provisions of your disability insurance policy you are being paid under, so that you are not caught unawares when your benefits (which you thought were lifetime benefits) are cut off after years of receiving benefits.
In our next post we will discuss another provision that limits lifetime benefits—the graded lifetime benefit rider.
[1] The World Bank, Life expectancy at birth, total (years), https://data.worldbank.org/indicator/SP.DYN.LE00.IN
The Importance of Regularly Reviewing Your Disability Policy
The new year is often a time for making resolutions and planning for the future. This should include reviewing your financial situation, including assessing whether you will be adequately prepared in the event that you become disabled and have to stop practicing. We recommend that you make a periodic review of your disability policies and evaluate:
- What type of policy(ies) do I have?
- Do I understand the terms and provisions of my policy(ies)?
- How much coverage do I have?
- Do I have enough coverage?
- Do I qualify for any increase options?
- Should I buy an additional policy(ies)?
Many physicians and dentists purchase their policies as residents or when they are first establishing their practice, and then file their disability insurance policies away and don’t think about them again until the unexpected happens and they need to file a disability claim. This is problematic, because financial needs and obligations change over time, and the income and standard of living for a resident is vastly different than that of a physician with a family 20 years down the road.
While insurance companies’ underwriting standards are typically structured in a way that prevents you from collecting the exact same amount of monthly income you were making pre-disability, your goal should be to get as close as possible. In other words, if you are a dentist earning $20,000 a month and need to file a claim, you don’t want to have to end up relying on a disability policy with a monthly benefit of $5,000 as your primary source of income.
Often disability insurance policies have future increase options that allow you to purchase additional coverage without changes to the terms of the existing policy. Typically, these options will only be available during certain discrete time periods set forth in the policy, so it’s important to read your disability insurance policy carefully to make sure you don’t miss out on the opportunity to take advantage of an increase option.
If your disability insurance policy does not have increase options and you’ve outgrown the monthly benefit amount, you can also purchase another policy to increase the total coverage you would receive if you filed a disability claim. However, if you’re going to be purchasing a new policy, you need to keep in mind that you must purchase a disability insurance policy that compliments you’re existing coverage, and does not cancel out your other policy or policies.
For example, some disability insurance policies contain provisions stating that a claimant cannot collect total disability benefits if he or she is working in another profession (a “no-work” provision). Other policies require the policyholder to work in some other capacity, in order to collect total disability benefits (a “work” provision). Thus, if you were to purchase a new disability insurance policy with a “work” provision, and your old disability insurance policy had a “no work” provision, one of the policies would be rendered useless (because it would be impossible to collect total disability benefits under both policies).
When purchasing a new disability insurance policy, it’s also important to keep in mind that disability policies have become increasingly more complex, restrictive and less favorable to policyholders over time. There is no longer a “standard” policy that every company sells—each policy will have it’s pros and cons, and it is therefore important to take your time to familiarize yourself with the disability insurance policy at the point of sale, so that you know what you’re purchasing. And if you didn’t pay close attention when you purchased the policy, or you can’t remember exactly what your policy says, you should review your disability insurance policy to assess whether it still meets your needs and make sure that you have an accurate understanding of the scope of your coverage.
Are There Options Besides A Trial When My Claim is Denied?
Reducing the risk of having to fight for disability benefits requires understanding the terms of your disability insurance policy from the beginning, carefully and thoroughly filling out the application, and ensuring accuracy and consistency in your claim packet and subsequent filings. As the saying goes, the best defense is a good offense, and the best way to avoid litigation is to file the disability claim correctly the first time.
Although filing a successful disability claim is not easy, it is the ideal. Unfortunately, insurance companies have a strong incentive to increase their bottom lines and often they practice aggressive tactics in improper attempts to justify the denial or termination of even a wholly legitimate disability claim. If your disability claim has been terminated or denied, it can seem overwhelming or hopeless to try to reverse the decision. In the event of a denial or termination, many insureds know they can sue their disability insurer and go to trial. Yet, even if you are ultimately successful in a lawsuit, litigation can sometimes drag on for years. While a lawsuit is pending, you’ll not only have legal expenses, but will also not be receiving disability benefits (and likely not be in a position to work to offset your expenses, due to the nature of your disability or your policy’s language). There are, however, some alternative options that can be attractive to both parties that policyholders may not be aware of, namely mediation and lump sum settlements.
Mediation
All too often we see legitimate disability claims denied or terminated, with the insurance company refusing to reconsider their position. If your disability claim is terminated, the company knows that it wields a lot of power over the denied individual, including the power of money, the power of time, the power of institutional knowledge, and the power to tolerate litigation. In other words, insurers calculate that spending money on even protracted litigation will end up being cheaper than continuing to pay disability benefits, and they know that many claimants will just give up and go away if they draw out court proceedings long enough.
While this might sound bleak, there can be alternatives to a full-fledged lawsuit that culminates in a trial (and potentially drawn-out appeals). One such method is mediation. Mediation is where the parties to a lawsuit meet with a neutral third party in an effort to settle the case.
For the most part, mediators are retired judges, or active or retired attorneys. The mediator reviews the case file and then meets with both parties, seeking to facilitate discussions between the parties and try to find common ground in order to reach an acceptable compromise. Because mediation is not binding, the mediator’s recommendation and any subsequent agreement between the parties is not final until the parties memorialize it by putting all the agreed upon terms in writing and signing the document.
Often the insurance company will offer to draft the agreement so they can have control over what the agreement says, and so it is important to stay engaged in the process even after the mediation has ended, in order to ensure that the parties’ agreement is accurately documented. The settlement agreement itself is a very important document, so you should be sure to take the time to carefully review it before signing, to be sure it encapsulates all the agreed upon terms.
It is also important to keep in mind that mediation typically does not result in a full restoration of disability benefits nor is not always successful. The non-binding nature of mediation means that if the insurance company low-balls and refuses to budge in its offer, the claimant may need to just walk away and resume litigation.
Lump Sum Settlement
Another way of avoiding trial is through negotiating a lump sum settlement. This typically occurs outside of the mediation setting, but sometimes requires the filing of a lawsuit before the insurance company is willing to come to the table. When this happens, your insurer agrees to buy out your disability insurance policy and you release your right to collect disability benefits under your policy and your insurer from any obligation to you. The buyout amount will be your disability insurance policy’s “present value” (i.e. the amount of money you could invest upon receipt, based on a determined interest rate, and end up with the same amount of money you would have received in disability benefits at the end of your policy), discounted by a percentage that is negotiated by the parties.
A buyout can be an attractive offer and can occur at any stage of the litigation process. A lump sum buyout could even be a preferable alternative to having disability benefits reinstated, as you would no longer have to deal with your insurer. Your disability benefit payments would cease being on hold pending the outcome of a trial and you could invest the lump sum in order to provide for your and your family’s future. In addition, unlike monthly disability benefits, the lump sum settlement you receive would be inheritable and available to be passed on to your heirs, should something happen to you.
There are, however, certain drawbacks to a lump sum buyout, including the fact that you and your disability insurers cannot accurately predict the future of the market with 100% certainty, so the calculations will only be a best estimate. If you are healthy and have lifetime benefits, you could also receive more money cumulatively over time if you were to stay on claim. So, while attractive, especially when faced with litigation, the pros and cons must be carefully weighted when considering lump sum buyouts during the litigation process.
We often see claimants who face the loss of their disability benefits simply give up and accept a denial, daunted by the thought of protracted litigation. While litigation may sometimes be the most advisable way to get benefits, and possibly punitive damages, there are other avenues to explore, advisably with the help of a disability insurance attorney, that can end in your retaining at least some of the disability benefits you stand to lose completely when an insurance company denies your disability claim.





